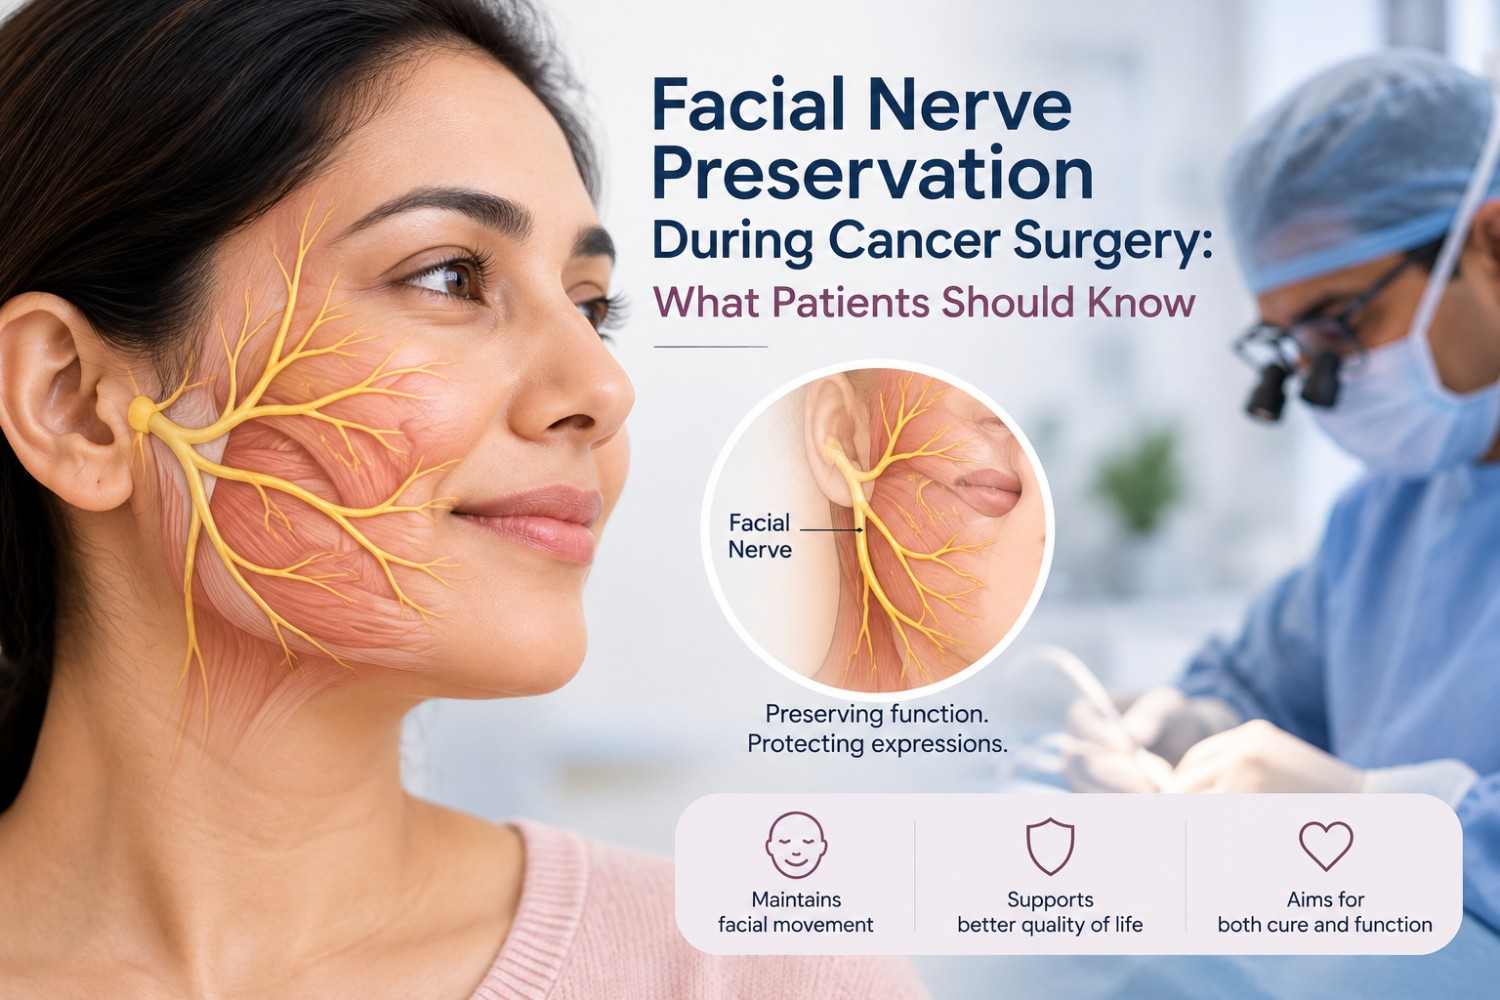
Facial Nerve Preservation During Cancer Surgery: What Patients Should Know
"Will I still be able to smile?"
It is one of the first questions people ask
once they hear that surgery is planned near the ear, jaw or salivary glands —
sometimes before they ask about the cancer itself. That is not vanity. The face
is how we greet people, how we are recognised, how we show what we feel. A
tumour is frightening in an abstract way; a crooked smile is frightening in a
way you can picture.
The nerve behind that worry is the facial
nerve, and it runs directly through territory that head and neck surgeons often
need to operate in. The honest answer is that in most operations it can be
identified and kept intact — but not in every operation, and not with a
guarantee. What follows is an explanation of how surgeons think about that
nerve, what genuinely puts it at risk, what can be done to protect it, and what
happens when protecting it is not possible.
What Is the Facial Nerve?
The facial nerve is the seventh cranial
nerve. It controls the muscles that move one side of your face — raising the
eyebrow, closing the eye, wrinkling the nose, smiling, and moving the lip and
chin. Each side of the face has its own facial nerve, so injury on one side
affects that side only.
The nerve leaves the skull through a small
opening just behind the earlobe, then almost immediately enters the parotid
gland — the large salivary gland that sits in front of and below the ear.
Inside the gland it divides like a river delta, usually into five main branches
that fan forward across the cheek and jaw to reach the facial muscles.
Two things follow from that anatomy, and
they explain almost everything in this article.
First, the nerve is not a single cord you
can simply move aside. By the time it reaches the cheek it is a network of fine
branches, some no thicker than a thread.
Second, the parotid gland does not sit
beside the nerve — it surrounds it. Surgeons describe the gland as having a
superficial lobe and a deep lobe, and the boundary between them is essentially
the plane of the facial nerve itself. Removing a parotid tumour therefore means
working around the nerve rather than away from it.
The facial nerve also carries fibres for
taste from the front of the tongue and for tear and saliva production, which is
why some people notice changes in those functions too.
Why Can Cancer Surgery Put the Facial Nerve at Risk?
Risk comes from proximity, not from cancer
surgery in general. The facial nerve is at meaningful risk only when the
operation takes place in the areas the nerve travels through or close to —
principally the parotid and other salivary gland
surgery, the region in front of and below the ear, the temporal bone, and
parts of the skull base.
Within those operations, risk varies
considerably depending on:
- Tumour location — a small lump
in the superficial part of the parotid sits above the nerve plane; a
deep-lobe tumour sits beneath it, so branches must be lifted and worked
around.
- Tumour size — larger tumours
stretch and flatten the branches, making them thinner and harder to see.
- Whether the tumour is benign or malignant — benign tumours usually push the nerve aside; some
cancers grow into or along it.
- Perineural spread — certain
cancers, adenoid cystic carcinoma being the best known, have a tendency to
track along nerves rather than simply pressing on them.
- Previous surgery in the same area —
scar tissue blurs the normal planes that surgeons rely on to find the
nerve.
- Previous radiotherapy —
irradiated tissue is firmer and less forgiving to dissect.
- Inflammation or infection —
repeated episodes can make tissues stick together.
One clinical sign carries particular
weight: facial weakness that was already present before any
operation. A tumour that has weakened the face has usually done so by involving
the nerve, and that raises concern about malignancy — although exceptions
exist, and it is a finding for your surgeon to interpret alongside imaging and
biopsy, not a diagnosis in itself.
It is worth saying plainly what this
section does not mean. Most head and neck cancer
surgery does not place the facial nerve at significant risk. An
operation on the tongue, floor of mouth, throat, larynx or thyroid is not a
facial nerve operation. If your surgery is in one of those sites, the risks you
should be reading about are different ones.
Can Surgeons Preserve the Facial Nerve During Cancer Surgery?
Yes — in most cases the facial nerve can
be identified and preserved, and preservation is the standard goal whenever it
can be achieved without compromising complete removal of the cancer. The
exception is a tumour that directly involves the nerve, where clearing the
cancer takes priority.
That ordering matters, and a good surgeon
will state it openly rather than leave it implied. Surgery is the treatment;
nerve preservation is a goal within that treatment. Leaving
cancer behind on a nerve in order to protect movement may preserve a smile for
a year and cost far more than that later.
In practice, most parotid and salivary
operations are not a choice between the nerve and the cancer at all. For benign
tumours and for many early cancers, the nerve is displaced rather than invaded,
and careful dissection separates the two. The dilemma arises in a minority of
cases, and imaging plus examination usually give warning that it may be coming.
How Is the Facial Nerve Protected During Surgery?
Protecting the facial nerve is a
sequence, not a single technique: imaging and planning before surgery, a
recorded baseline examination, deliberate identification of the nerve trunk at
a known anatomical landmark, unhurried dissection along each branch under
magnification, and — in selected cases — electrical nerve monitoring to confirm
what the surgeon is seeing.
Preoperative imaging and planning
MRI is generally the most informative scan
for soft-tissue tumours of the parotid and salivary glands, because it shows
the relationship between the tumour and the expected plane of the nerve, and
can suggest deep-lobe extension or spread along a nerve. CT adds detail about
bone, which matters near the temporal bone and skull base. Ultrasound-guided
needle sampling often provides a preliminary idea of the tumour type.
None of these tests images the fine
branches of the facial nerve directly. They inform the plan; they do not
replace what is found in the operating room.
Baseline facial nerve examination
Before surgery, facial movement is assessed
and recorded — eyebrow lift, tight eye closure, smile, lip pursing, lower lip
movement. Surgeons commonly grade this using the House–Brackmann scale, which
runs from Grade I (normal) to Grade VI (complete paralysis). Without that
baseline, no one can say afterwards what changed.
Identifying the nerve during surgery
Rather than searching for the nerve where
the tumour is, surgeons work backwards from a predictable landmark near the
ear, find the main trunk in normal tissue, and then follow it forwards branch
by branch. Working from known anatomy into unknown territory is safer than the
reverse. In some situations the approach is reversed deliberately — a distal
branch is found first and traced back — when scarring or tumour position makes
the standard landmark unreliable.
Meticulous dissection
The dissection itself is slow, bloodless
work carried out with fine instruments and magnification, separating tissue in
the plane of the nerve rather than across it. Diathermy and other heat-based
instruments are used sparingly near branches, because heat injures nerves that
were never cut.
Intraoperative facial nerve monitoring
Monitoring uses small electrodes in the
facial muscles connected to a machine that signals when a nerve branch is
stimulated or irritated. It helps confirm that a structure is nerve before it
is divided, and warns when instruments are closer than expected.
Published meta-analyses of parotid surgery
have found monitoring to be associated with a lower rate of immediate
postoperative facial weakness, and more recent pooled analyses have also
reported benefit for longer-term dysfunction, though the evidence on permanent
weakness has been less consistent across studies.
What monitoring cannot do is guarantee an
intact nerve. It does not prevent a nerve from being stretched, devascularised
or heat-injured, it cannot make a nerve separable from a cancer that has grown
into it, and it does not replace anatomical knowledge. It is an aid to a
careful surgeon, not a substitute for one.
When the Facial Nerve Cannot Be Preserved
Sometimes the tumour is attached to, or
growing into, the nerve. In that situation, separating the two would mean
cutting through cancer and leaving disease behind, and the involved segment has
to be removed with the specimen.
This is uncommon, and it is not a surprise
decision made casually. It is usually anticipated from three things together:
facial weakness present before surgery, imaging suggesting involvement, and a
biopsy showing a cancer type known to behave that way. Where it is a realistic
possibility, it should be discussed before surgery, not explained afterwards —
including which branches might be affected and what reconstruction would be
considered.
Where only some branches are involved, the
uninvolved ones are preserved. Losing one branch is not the same as losing the
nerve, and the functional result differs accordingly.
When a segment is removed, repair is
usually considered in the same operation wherever it is technically feasible
and clinically appropriate, rather than being deferred.
What Happens If the Facial Nerve Is Injured or Affected?
Not all facial weakness after surgery means
the nerve was cut. The commonest pattern by far is temporary weakness in a
nerve that is anatomically intact — bruised, stretched or handled during
dissection, and still connected.
Possible outcomes range across a spectrum:
- Temporary weakness (neuropraxia) —
the nerve is intact but not conducting normally. Function typically
returns over weeks to a few months.
- Partial weakness affecting one or two branches — most often the branch to the lower lip or to the
eyelid, producing an asymmetric smile or slower blink rather than a still
face.
- Prolonged weakness — recovery
over many months where the nerve fibres themselves were damaged but the
sheath remained continuous, allowing regrowth.
- Complete paralysis of that side —
where the nerve was divided or removed.
Published series of parotid surgery report
temporary facial weakness in a substantial minority of patients and permanent
weakness in a much smaller proportion, but the figures vary widely between
studies because the mix of benign and malignant tumours, the extent of surgery
and the method of assessment all differ. Rates from a series dominated by
advanced cancers say very little about a small benign lump — which is why your
surgeon's estimate for your operation is more meaningful than
any published average.
Facial nerve situations and what they may mean
|
Situation |
What it may mean |
How it may be managed |
|
Nerve clearly separate from tumour |
Standard dissection; low risk of lasting
change |
Preservation with routine post-op checks |
|
Nerve stretched or closely adherent |
Higher chance of temporary weakness |
Preservation, careful handling,
monitoring of recovery |
|
Temporary post-operative weakness |
Nerve intact but not conducting normally |
Observation, eye protection if blink is
affected, physiotherapy if advised |
|
One branch involved by tumour |
Selective loss possible |
Sacrifice of that branch only; repair
considered |
|
Main trunk invaded by cancer |
Complete removal requires nerve sacrifice |
Immediate nerve graft or reanimation
where appropriate |
|
Nerve removed, repair not feasible
immediately |
Reconstruction may be staged |
Static procedures, eye care, later
reanimation options |
This table describes possibilities, not
predictions. Individual management depends on findings at surgery and on the
final pathology.
Can Facial Weakness After Surgery Improve?
Often, yes. Weakness caused by handling
or stretching of an intact nerve commonly improves over several weeks to a few
months, and recovery can continue for longer. Weakness caused by a nerve that
was divided or removed does not recover on its own and is managed with
reconstruction and rehabilitation instead.
Recovery is gradual and usually uneven —
the eye may recover before the smile, or the forehead before the lip. Surgeons
generally reassess at intervals over the first six to twelve months before
drawing conclusions, because late improvement is well recognised.
Two things matter during that period.
Eye protection comes first. If the eyelid does not close fully, the surface of the eye
loses its natural protection and can dry, ulcerate or become infected.
Lubricating drops during the day, ointment and taping at night, and
ophthalmology review where needed are not optional comfort measures — they
protect sight. Any redness, pain or blurring in that eye deserves prompt
attention.
Rehabilitation has a role. Structured facial physiotherapy and neuromuscular retraining
are used in selected patients to improve control and reduce unwanted
co-movement as the nerve recovers. Forceful, unsupervised exercise is not
helpful.
No one can responsibly promise a particular
degree of recovery in advance. What can be offered is honest assessment, a
clear follow-up plan, and prompt action if things stall.
What If the Facial Nerve Has to Be Removed?
Options exist, and they are best considered
early — ideally at the same operation.
Direct repair joins the two ends when a short segment is missing and the
ends reach without tension.
Nerve grafting bridges a longer gap with a length of nerve taken from
elsewhere, commonly the greater auricular nerve in the neck or a sensory nerve
from the arm or leg. Regrowth is slow: fibres regenerate over months, and first
movement is typically seen somewhere in the range of six months to a year.
Published series report that grafting commonly restores tone, symmetry at rest
and meaningful but incomplete voluntary movement — often around House–Brackmann
Grade III — rather than a normal face.
Nerve transfer connects a nearby healthy nerve, such as the nerve to the
chewing muscle, to the facial nerve system. Reinnervation tends to appear
earlier than with a graft.
Static procedures — such as eyelid weights and support of the lower lid, brow or
cheek — do not restore movement but protect the eye and improve symmetry, and
are often combined with the above. Longer-term dynamic options fall under facial nerve
reanimation, and where larger tissue defects are involved these decisions
are made alongside reconstruction
after cancer surgery.
Which option suits a given patient depends
on how much nerve remains, whether the facial muscles are still viable, planned
radiotherapy, general health and the overall treatment plan. Rehabilitation
strongly influences the final result and should be treated as part of the
reconstruction rather than an afterthought.
Which Cancer Surgeries May Involve Facial Nerve Considerations?
The facial nerve is a genuine consideration
mainly in:
- Parotid tumour surgery, benign or
malignant — the single most common context. This is the focus of a
dedicated page on parotid
tumour surgery with facial nerve preservation.
- Selected other salivary gland tumours, where a branch runs close to the operative field — the branch
to the lower lip is the one at risk in submandibular gland surgery.
- Ear
and temporal bone tumour surgery, where the nerve runs within
bone.
- Selected skull base tumours,
depending on the route of approach.
- Skin cancers in front of or below the ear that extend deeply.
- Revision or salvage surgery in
a previously operated or irradiated field.
Surgery for cancers of the tongue, floor of
mouth, throat, voice box or thyroid does not normally place the facial nerve at
meaningful risk. If you have been reading about facial paralysis while awaiting
one of those operations, the concern may not apply to you — worth confirming at
your next appointment.
What Determines Your Individual Risk?
Your risk is a combination of:
- Where the tumour sits relative
to the plane of the nerve — superficial, deep, or both.
- Tumour size and how much the
branches are stretched.
- Pathology — benign versus
malignant, and the specific cancer type.
- Imaging findings, particularly any
suggestion of nerve involvement or perineural spread.
- Stage and extent of disease
locally.
- Facial nerve function before surgery — existing weakness is a significant finding.
- Previous treatment — earlier
surgery or radiotherapy in the same field.
- Findings at operation — the
final assessment is made with the nerve in view.
If you want a considered view on your own
scans and reports before committing to surgery, a formal review
of your biopsy and scans is a reasonable step, and second opinions are
routine in head and neck oncology rather than a sign of distrust.
Questions to Ask Before Cancer Surgery
Take these to your consultation. Write the
answers down — few people retain them otherwise.
- How close is my tumour to the facial nerve, and is it
superficial or deep?
- Does my MRI or CT suggest that the nerve is involved, or only
displaced?
- What is your estimate of temporary facial weakness in my case,
and what would it look like?
- What is the chance of permanent weakness?
- Will intraoperative nerve monitoring be used?
- What will you do if the tumour turns out to be stuck to the
nerve?
- If part of the nerve has to be removed, will repair or grafting
be done in the same operation?
- How will my facial function be checked afterwards, and at what
intervals?
- If my eye does not close fully, what eye care will I need and
who will supervise it?
- Is radiotherapy likely afterwards, and would that affect nerve
recovery or reconstruction?
When to Contact Your Doctor After Surgery
Contact your surgical team without waiting
for your scheduled appointment if you notice:
- New or worsening facial weakness that appears after an
initially normal recovery
- Inability to close the eye fully, or any pain, redness,
watering or blurred vision on that side
- Increasing swelling, redness, heat or discharge at the wound
- Fever
- A collection of fluid or clear leakage from the wound
- Severe or escalating pain not controlled by the medication you
were given
Weakness that is present immediately after
surgery and is slowly improving is a different situation — expected in many
cases and best reviewed at your planned follow-up. If you are unsure which of
the two you are experiencing, ask rather than wait.
This article is for general educational
purposes and does not replace an individual consultation, examination,
diagnosis, or treatment plan from a qualified healthcare professional.
About the author. Dr. Karan Gupta is a Head & Neck Surgical Oncologist and
robotic head and neck surgeon practising in Delhi NCR. He holds MBBS, MS and
DNB qualifications with gold medals in all three, completed fellowship training
in Head & Neck Surgical Oncology at Tata Memorial Hospital, Mumbai and HCG,
Ahmedabad, and a fellowship in Robotic Head & Neck Surgery through the
Vattikuti Foundation, Michigan, USA. He is an Intuitive Surgical (USA)
certified robotic head and neck surgeon. Full profile
Reviewed: 18 September 2026. This article is reviewed periodically and updated as evidence changes.
FAQ
Can cancer surgery damage the facial
nerve?
It can, but only in operations that
take place where the nerve runs — mainly parotid and some other salivary gland
surgery, temporal bone surgery, and selected skull base procedures. In most of
these operations the nerve is identified and preserved. Temporary weakness from
handling or stretching is more common than permanent injury, and surgery for
cancers of the tongue, throat, voice box or thyroid does not usually put the
facial nerve at meaningful risk.
How do surgeons protect the facial nerve
during surgery?
By planning from imaging, recording
baseline facial movement, finding the main nerve trunk at a known landmark in
normal tissue, then tracing each branch forward under magnification with fine
instruments and minimal use of heat near the nerve. Electrical nerve monitoring
may be used in selected cases to confirm that a structure is nerve. These
measures reduce risk; none of them eliminates it.
Is facial weakness after surgery always
permanent?
No. The most common pattern is temporary
weakness in a nerve that remains intact, caused by stretching, handling or
swelling during the operation. This typically improves over weeks to a few
months, sometimes longer. Permanent weakness generally follows division or
removal of the nerve, or a severe injury to the fibres — which is far less
common than temporary weakness.
Can the facial nerve recover after
surgery?
An intact nerve usually does recover,
though the pace varies and different parts of the face may return at different
times. Where fibres were damaged but the nerve remained continuous, regrowth is
slow and recovery may take many months. A nerve that was cut or removed does
not recover on its own; function in that situation is addressed through repair,
grafting, nerve transfer or reanimation procedures.
Does nerve monitoring prevent facial
nerve injury?
No. Monitoring helps a surgeon confirm that
a structure is nerve and warns of nearby irritation, and studies in parotid
surgery have associated its use with lower rates of immediate postoperative
weakness. But it cannot prevent stretch or heat injury, cannot separate a nerve
from cancer that has grown into it, and does not replace anatomical knowledge
and careful dissection. It is an aid, not a guarantee.
What happens if cancer has grown into
the facial nerve?
Complete removal of the cancer takes
priority. The involved segment of nerve is removed along with the tumour, while
uninvolved branches are preserved wherever possible. Repair is usually
considered in the same operation where technically feasible — direct join,
nerve graft, or nerve transfer — and static procedures may be added to protect
the eye and improve symmetry.
Can facial nerve function be restored
after the nerve is removed?
Meaningful improvement is often
achievable, though a completely normal face is not a realistic expectation.
Grafting and nerve transfers can restore resting tone, symmetry and some
voluntary movement; published series commonly describe partial rather than full
recovery. Static procedures protect the eye and improve appearance. Results
depend on the length of nerve lost, muscle viability, planned radiotherapy and
rehabilitation.
How long can facial nerve recovery take?
Temporary weakness after an uncomplicated
operation often improves within a few weeks to three months. Recovery from more
significant injury to an intact nerve can continue over six to twelve months.
After nerve grafting, first movement usually appears somewhere between about
six months and a year, with continued change for a year or more afterwards.
Surgeons generally avoid drawing final conclusions before that point.